


GLP-1 therapies crossed two thresholds at once in September 2026, and neither one fits the story investors have been telling themselves. The first is biological: children as young as six showed a 40% reclassification out of obesity in a Phase 3 trial. The second is technological: a single implantable device sustained roughly 20% body mass reduction beyond six months in preclinical models.
The established investor read on GLP-1 has been a two-horse race between Novo Nordisk and Eli Lilly, fought on volume, payer access, and pipeline depth. These two developments complicate that frame. Pediatric approvals could open a structurally distinct patient population, while implantable delivery targets the adherence gap that is quietly eroding the real-world value of the entire injectable category.
Here is what these developments actually change about the GLP-1 investment thesis, and what still needs to happen before they represent genuine opportunity rather than speculative noise. The point is to leave you knowing which variables to track, not just what was announced.
What the STEP Young trial actually proves, and what it does not
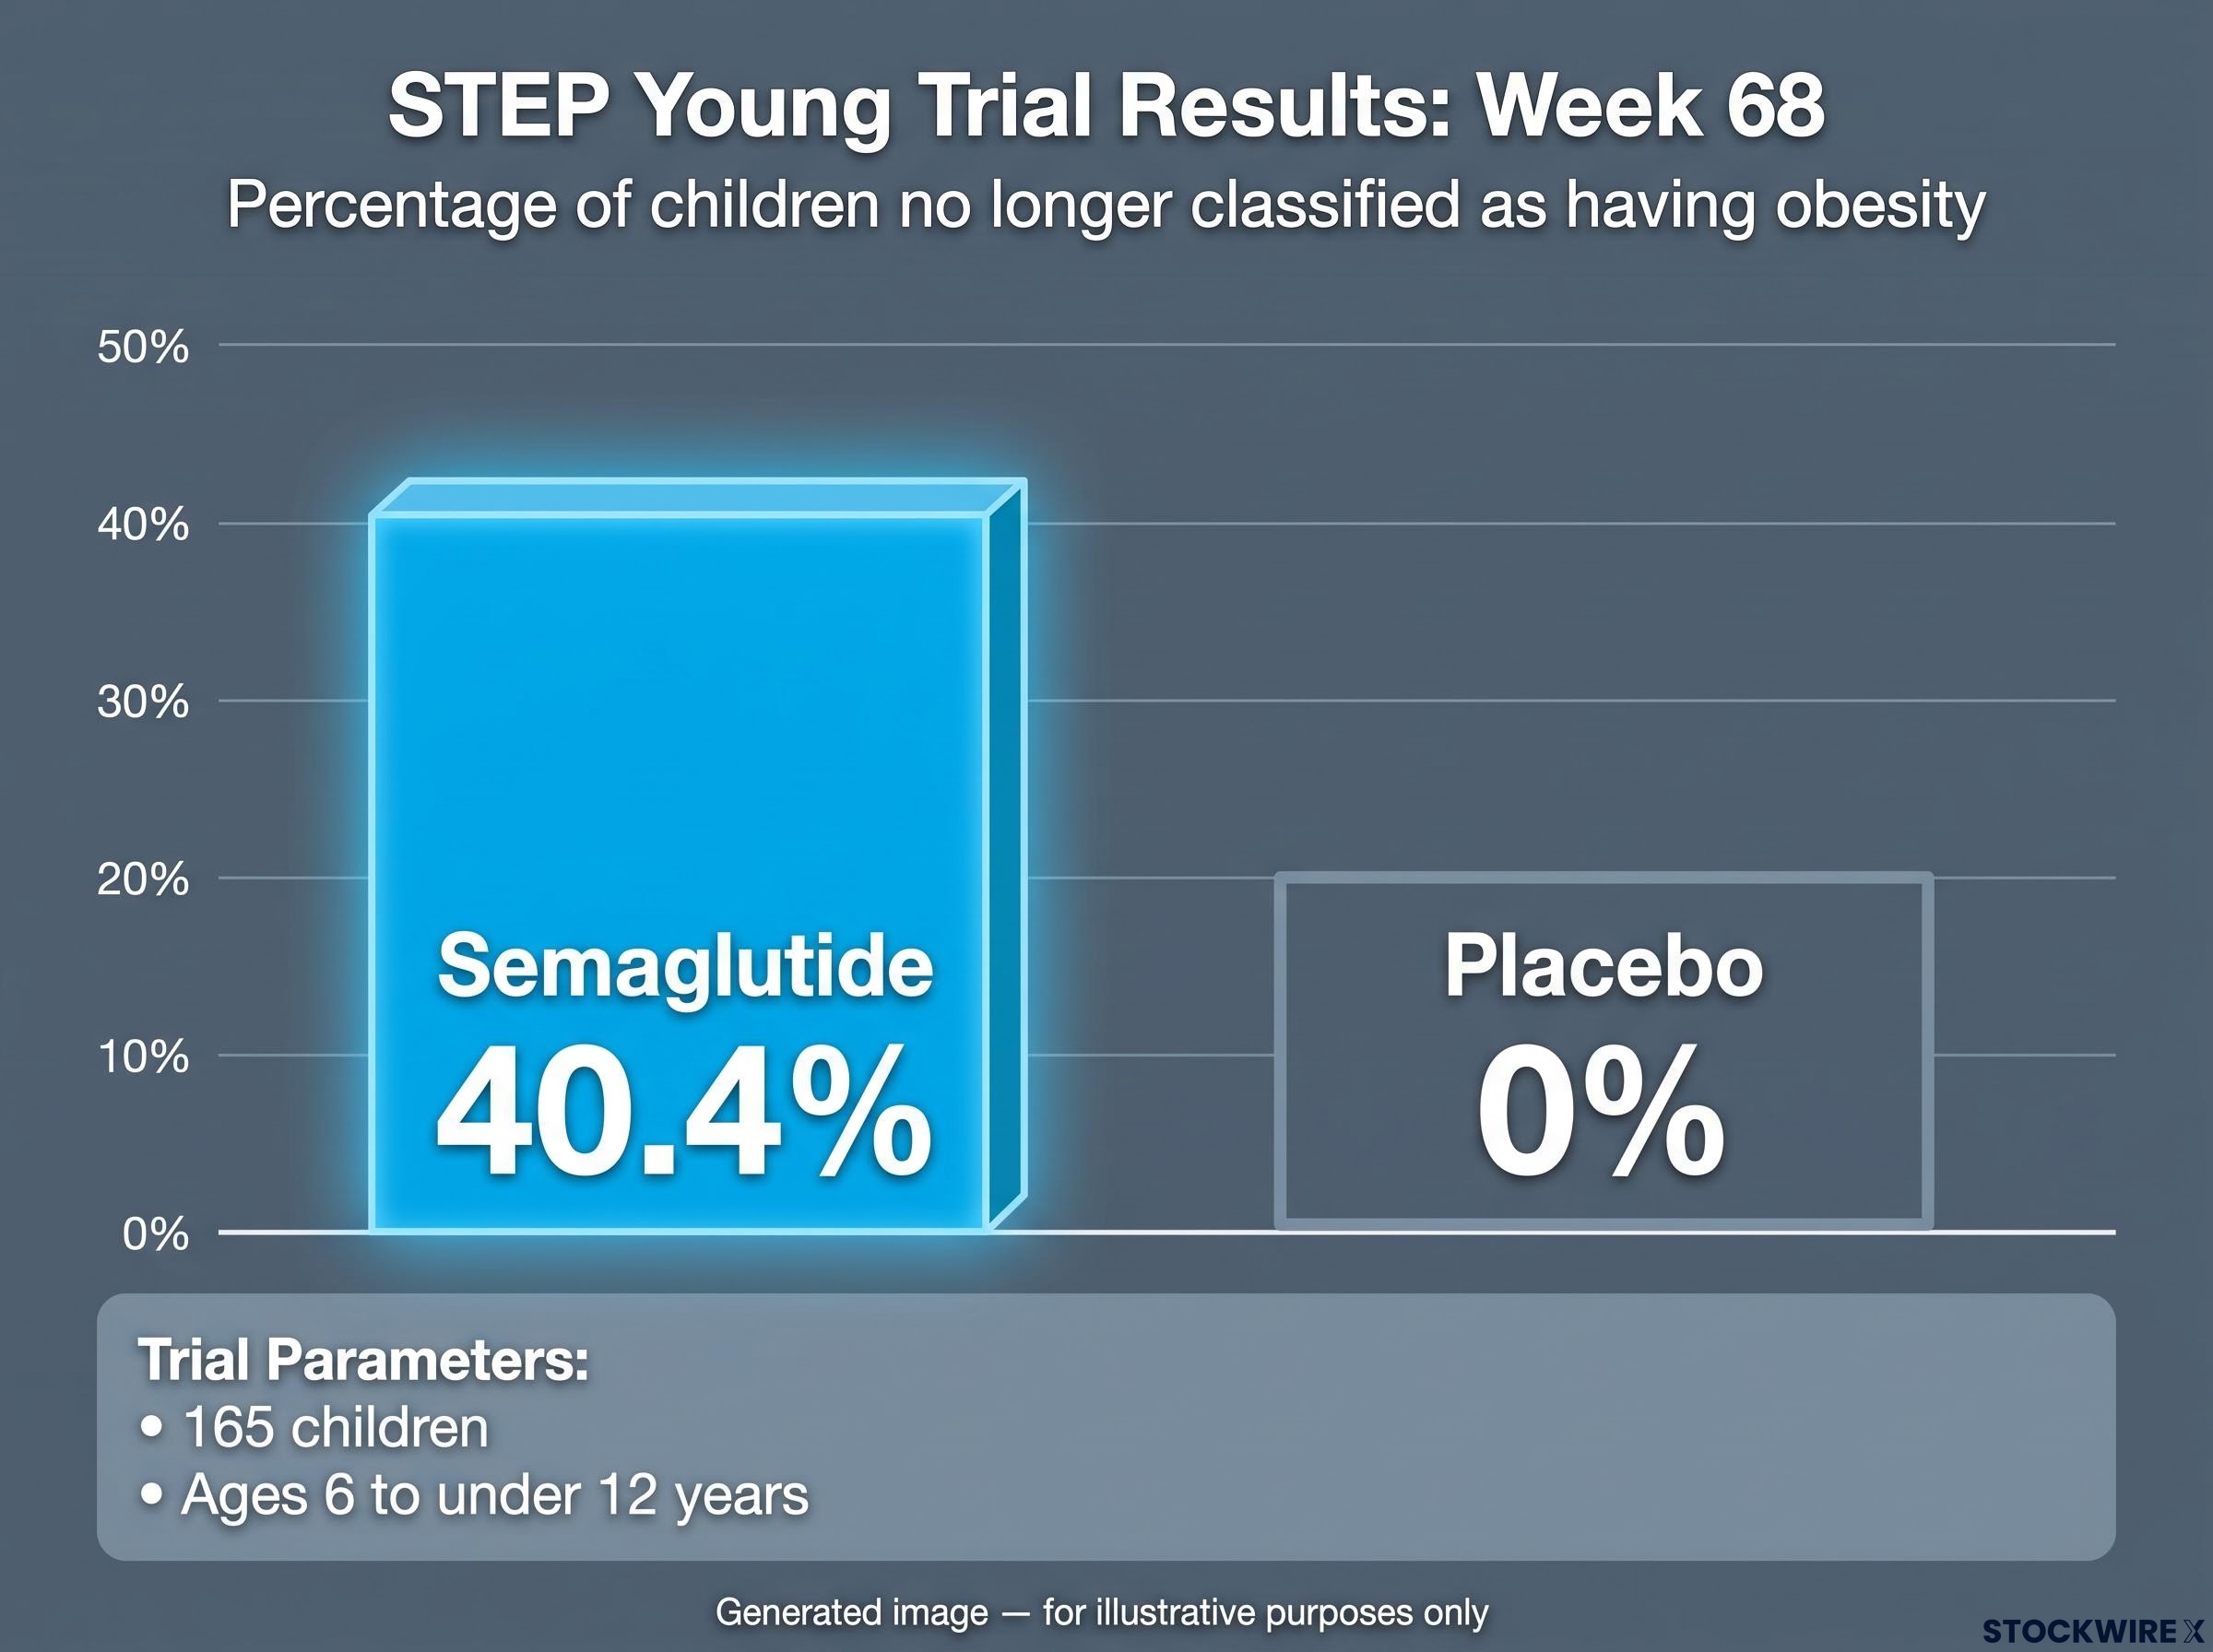
The number that will draw headlines is stark. In STEP Young, a Phase 3 trial of once-weekly semaglutide plus lifestyle intervention, 40.4% of children treated with the drug were no longer classified as having obesity by week 68. In the placebo group, that figure was 0%.
The single most striking result 40.4% of semaglutide-treated children dropped below the obesity threshold at week 68, versus 0% on placebo.
That is a landmark in pediatric obesity science. Novo Nordisk announced the first results on 7 September 2026, and the trial parameters underline how deliberate it was.
Novo Nordisk’s STEP Young announcement, published on 7 September 2026, provides the primary top-line data on which the pediatric thesis rests, including the 40.4% reclassification figure and the preliminary safety assessment confirming no new signals for growth or pubertal development.
- Age range: 6 to under 12 years
- Participants: 165 children, more than 85% with class 2 or class 3 obesity at baseline
- Duration: 68 weeks
- Primary endpoint: significantly greater BMI reduction versus placebo, met
- Safety: consistent with prior pediatric and adult semaglutide trials, with no new signals for growth or pubertal development
Full peer-reviewed data are expected at ObesityWeek 2026. What matters for your read of the thesis is the distance between this result and anything resembling revenue.
The regulatory and safety hurdles between trial and approval
As of mid-September 2026, no GLP-1 receptor agonist is authorised for obesity in children under 12 anywhere. Wegovy is approved for ages 12 and older. STEP Young does not change that status; it opens a door that regulators will walk through slowly, if at all.
Pediatric GLP-1 reviews flag specific concerns that demand long-term data: thyroid C-cell tumour risk based on animal studies, potential effects on bone mineralisation, and growth trajectory monitoring during critical developmental years. These are the reasons a single 68-week readout does not clear the path.
The long-term follow-up study, listed on ClinicalTrials.gov as NCT05726227, was marked “active, not recruiting” as of 9 September 2026. That means data is still maturing, not concluding. The liraglutide precedent is instructive: earlier trials in 6-12-year-olds achieved BMI reduction, but investigators cautioned that long-term growth effects remained uncertain.
Endocrinology guidance from 2025-2026 recommends GLP-1 use in under-12s only on a case-by-case basis, with careful risk-benefit assessment. Layer in informed-consent complexity for minors and equity concerns around payer coverage, particularly Medicaid, and the commercial runway becomes years long. If you are pricing pediatric semaglutide as a near-term earnings catalyst, you are running well ahead of where the evidence and the approval pathway actually sit.
When big ASX news breaks, our subscribers know first
The NanoPortal implant thesis: solving adherence or adding complexity?
The problem implantable delivery is built to solve is not efficacy. It is that patients stop taking the drug. Real-world one-year persistence for injectable GLP-1s sits in the 40-60% range, and the gap between what trials show and what routine care delivers is where the category quietly loses value.
The stat that anchors the entire adherence argument Analysis cited by Intarcia Therapeutics estimates that poor adherence with pills and injections accounts for roughly a 75% reduction in real-world efficacy compared with clinical trials.
That is the structural inefficiency Vivani Medical is targeting with NPM-139, a miniature semaglutide implant built on its NanoPortal platform. According to Vivani’s corporate materials, the device is designed to release drug continuously for six to twelve months. Preclinical animal models showed approximately 20% body mass reduction sustained beyond six months from a single implant.
The first-in-human data is close. Vivani’s SLIM-1 trial in Australia dosed its final participant on 6 August 2026, with top-line results projected for November 2026.
- Design: open-label, randomised, active-comparator controlled
- Participants: 20 GLP-1-naive subjects, 10 per group
- Comparison: low-dose NPM-139 implant versus weekly Wegovy 0.25 mg
- Duration: four weeks
- Primary endpoints: safety, tolerability, pharmacokinetics, with weight loss also measured
Here is how the delivery formats compare on the metrics that decide whether an implant earns its place.
| Delivery format | Duration | Adherence (1-year) | Key advantage | Key risk |
|---|---|---|---|---|
| Weekly injection (Wegovy) | Weekly dosing | 40-60% | Established efficacy and approval | Behavioural drop-off, needle aversion |
| Daily oral | Daily dosing | Variable, dosing burden | No injection required | Daily adherence barrier |
| Implant (NPM-139 target) | 6-12 months per device | Target 70-80% | Removes day-to-day adherence entirely | Unproven in humans, procedural |
The commercial logic follows directly. If Vivani can demonstrate one-year adherence of 70-80% against the 40-60% injectable baseline, that alone could justify a premium pricing model even where the per-dose semaglutide cost is comparable.
Novo Nordisk is watching. On 7 July 2026, Vivani announced a non-exclusive internal evaluation agreement, allowing Novo to assess the implants Vivani prepares. There is no exclusivity, no co-development commitment, and no commercialisation rights attached.
If SLIM-1 delivers a clean safety and pharmacokinetic profile in November, it validates the scientific plausibility of implantable GLP-1 delivery. What it will not tell you is whether Novo converts an evaluation into a partnership, or whether real-world adherence gains materialise at the level the pricing thesis assumes.
Novo Nordisk’s competitive position and why these developments matter to its strategy
The scale involved explains the urgency. Novo Nordisk’s two flagship semaglutide products generated roughly DKK 206 billion in combined sales in 2025, split across diabetes and obesity markets.
| Product | Indication | 2025 sales (DKK) | 2025 sales (approx. USD) |
|---|---|---|---|
| Ozempic | Type 2 diabetes | DKK 127.09 billion | US$15.4 billion |
| Wegovy | Obesity | DKK 79.11 billion | US$7.1 billion |
| Combined | GLP-1 franchise | ~DKK 206 billion | ~US$21.9 billion |
That franchise is under pressure from several directions at once.
- Market share: S&P Global Market Intelligence projected in August 2025 that Eli Lilly is likely to overtake Novo in the GLP-1 weight-loss market, driven by Mounjaro and Zepbound.
- Growth deceleration: the same analysis forecast Ozempic growth slowing to around 7%, with Wegovy growth also cooling beyond 2025.
- Compounded semaglutide: cheaper unauthorised versions are pulling volume away, a headwind Morningstar noted in July 2025 as costing Novo GLP-1 share slightly faster than expected.
- Payer access: Novo’s push for exclusive payer contracts and the cash-pay market is compressing margins even as volume holds.
The market share contest is already tilting before pediatric or implant developments reach commercial scale: Lilly’s Zepbound captured 71% of new U.S. obesity prescriptions by Q3 2025, while Novo’s oral GLP-1 market share remains dominant in the pill segment, where Lilly’s dual-receptor advantage does not apply.
Seen against that backdrop, the pediatric program and the Vivani evaluation stop looking like isolated research and start looking like positioning. STEP Young opens a patient population Lilly has not yet contested. Implantable delivery offers a way to defend semaglutide’s position once oral competitors and generics intensify the fight.
What the evaluation agreement signals, and what it does not
The structure of the Vivani deal is the tell. It is non-exclusive, carries no licensing terms, and confers no commercialisation rights. It is explicitly an evaluation.
Large pharmaceutical companies routinely test emerging delivery platforms before committing. Historically these agreements validate scientific interest, but they do not guarantee a full partnership or acquisition, and no published statistics quantify how often evaluation converts to a commercial deal in implantable peptide delivery.
For you, the read is dual. Novo’s scale means incremental pipeline moves carry enormous optionality, but the fact that it is actively evaluating alternatives signals genuine competitive squeeze. Confidence and urgency are both in the frame, and the distinction matters for how you size your exposure.
For readers wanting to understand how the market is already pricing innovation risk into Novo’s valuation, our dedicated guide to Novo Nordisk’s Q2 2026 results covers how CagriSema’s underwhelming readout and oral Wegovy’s revenue miss reshaped investor expectations ahead of these September developments.
Calibrating the risk: what investors should actually be watching
The opportunity is real. The question is whether it is investable at the current stage of evidence, and that turns on three distinct risk categories, each with a specific milestone that will confirm or break the thesis.
- Regulatory and long-term safety risk (pediatric). No GLP-1 receptor agonist is approved for under-12s as of September 2026. STEP Young’s long-term follow-up is still pending, and guideline bodies recommend case-by-case use only. The thesis validates only if follow-up safety data hold and guidelines evolve, a multi-year process.
- Commercial and adherence-assumption risk (implant). The premium pricing case depends on implants materially beating the 40-60% injectable adherence baseline. But discontinuation is also driven by adverse effects, cost, and inadequate lifestyle support, meaning an implant may not fix the full attrition problem. If real-world adherence does not clearly exceed injectables, the rationale weakens.
- IP, capital, and partnership-dependency risk (Vivani). An August 2026 analysis by Cypris AI flags high freedom-to-operate legal costs and a dense GLP-1 patent landscape as major hurdles for smaller delivery-platform firms. The Novo agreement compounds this: it is non-exclusive with no commercialisation commitment, leaving Vivani’s commercial outcome contingent.
The value here is that each risk maps to a concrete event rather than a headline.
The nearest-term binary catalyst SLIM-1 top-line data, projected for November 2026, is the first human read on whether implantable GLP-1 delivery is safe and pharmacokinetically viable.
The specific signals worth tracking:
- SLIM-1 top-line data (November 2026), the first human safety and pharmacokinetic read
- ObesityWeek 2026, where full peer-reviewed STEP Young data will be presented
- Any evolution in the Novo-Vivani agreement structure, from evaluation toward licensing or co-development
Map your watch-list to those events, not to the announcements that have already been priced, and you will be positioned to act before the market re-rates.
Where the GLP-1 expansion story goes from the evidence available today
Both developments are genuine, and both are early. Pediatric semaglutide and implantable delivery carry distinct timelines and risk profiles, and they should be treated separately rather than bundled into a single bull case.
GLP-1 market penetration remains remarkably shallow despite the category’s commercial scale: global uptake sits at roughly 2% of people with obesity, a figure that contextualises why both pediatric expansion and adherence-improving delivery formats carry genuine long-term strategic weight even at early evidence stages.
- Pediatric pathway: STEP Young met its endpoint, but under-12 approval is likely years away even under favourable follow-up, with payer coverage and guideline adoption adding further delay.
- Implant pathway: SLIM-1 is Phase 1. Phase 2 and Phase 3 stand between NPM-139 and any approval, making commercial launch a multi-year prospect even on a clean development path.
Two events will materially narrow the uncertainty: the November 2026 SLIM-1 readout and the full STEP Young presentation at ObesityWeek 2026. Those are the dates that update the thesis.
The competitive landscape context
The absolute prize explains why Novo is investing across both fronts. A franchise generating roughly DKK 206 billion in 2025 makes even early-stage delivery and indication innovation strategically worthwhile as a moat-building play against compounded semaglutide and Lilly’s advance.
Lilly’s dual-action drugs, Mounjaro and Zepbound, are not directly implicated in either the pediatric or implant story, keeping this a Novo-centric narrative for now. The broader takeaway is that competitive intensity is now driving innovation across delivery formats and patient populations at the same time, which widens the opportunity set but makes the analysis harder than simply choosing between Novo and Lilly.
The GLP-1 story is far from over. The next chapter, though, is being written in clinical data rooms and regulatory dossiers, not yet in quarterly revenue lines, and allocating with that in mind is the calibrated position.
This article is for informational purposes only and should not be considered financial advice. Investors should conduct their own research and consult with financial professionals before making investment decisions. Past performance does not guarantee future results, and financial projections are subject to market conditions and various risk factors. Forward-looking statements regarding clinical trials, regulatory approvals, and commercial partnerships are speculative and subject to change based on trial data, regulatory decisions, and company performance.







