Your immune system’s virus sensors spend every day surrounded by material that looks almost exactly like the enemy they were built to destroy. They rarely open fire. The real puzzle is not why your body attacks invaders. It is how an immune regulatory mechanism keeps those sensors quiet the rest of the time.
That restraint matters more than it first appears. The same piece of biology can explain two very different failures: an immune system that turns on your own tissue, and one that looks straight past a growing tumour.
This is the lens for understanding the science behind Noxopharm (ASX: NOX), published in Nature Immunology in February 2026. The paper describes a natural brake on two key immune sensors, and the company is trying to push that brake in both directions.
Here you will see how the brake works, watch it fail one way and hold too firmly the other, and get a clear line between what has been proven and what has not.
Why do the immune system’s viral sensors not attack the body?
Start with two sensors called TLR7 and TLR8. TLR stands for Toll-like receptor, a protein that detects signs of infection. These two sit inside compartments within your immune cells, where they watch for viral RNA, the genetic material many viruses carry.
When they detect it, they trigger a response designed to destroy the invader. That is exactly what you want during an infection.
A discrimination problem with look-alike evidence
Here is the difficulty. Your own RNA and viral RNA are chemically very similar, so the sensors cannot simply check for a “foreign” label.
Worse, cells in your body are forever degrading and reusing their own RNA. TLR7 and TLR8 are therefore never free of contact with material that closely resembles their intended targets.
If they fired every time they met it, you would live with chronic inflammation aimed at yourself. In effect, that describes autoimmune disease, and lupus, a condition in which the immune system attacks the body’s own tissues, is a leading example.
The core question If your sensors are always seeing look-alike RNA, what stops them from firing at you?
The answer reframes how you should think about immune health. Tolerance of your own tissue is not the default state. It is actively maintained, which is why a failure in that maintenance can make you sick.
When big ASX news breaks, our subscribers know first
What is the RNA brake that Nature Immunology identified?
In February 2026, Nature Immunology published the answer. The journal is described as the top-ranked peer-reviewed title for primary immunology research, so the bar for acceptance is high.
The work was led by Professor Michael Gantier at the Hudson Institute of Medical Research in Melbourne, with international collaborators and three Noxopharm employees among the authors. Lead author Arwaf Alharbi and Gantier sit at either end of a 28-person author list. The paper grew out of a laboratory Gantier founded in 2015, reflects more than six years of research, and builds on two decades of his work in autoimmunity.
The mechanism, in plain terms:
- Your body continually produces very short RNA fragments carrying a chemical tag called 2′-O-methyl, a small modification to the RNA’s sugar backbone.
- These tagged fragments, many derived from abundant ribosomal RNA, bind directly to TLR7 and TLR8 at a third binding site separate from the two previously known ones.
- Once bound, they hold the sensors in an inactive shape, so the sensors cannot signal even when stimulating RNA is present.
In effect, your own debris carries a “stand down” signal. That is the brake.
The Nature Immunology paper shows that short 2′-O-methyl RNA fragments act as natural antagonists of TLR7 and TLR8, which is why you can treat this finding as a validated mechanism rather than a company claim.
Professor Arthur Krieg of the UMass Chan Medical School RNA Therapeutics Institute is a foundational figure in the study of immune-stimulating oligonucleotides, which are short, synthetic strands of genetic material. His view reached the public through Noxopharm’s announcement.
Independent assessment Professor Arthur Krieg characterised the work as changing the field’s understanding of how viral-infection sensors are normally blocked to prevent autoimmunity.
What the paper does and does not establish
This is the most credible fact in the whole story, so be precise about it. The paper validates a biological mechanism. It does not validate any drug built on that mechanism.
The live-animal work in the study was also done in mice. That is why independent experts could assess it on its own terms: it is a finding about how healthy immunity works, separate from any commercial programme.
When the natural brake is too weak: a topical approach to lupus
Once you know the brake exists, the first therapeutic idea almost writes itself. If the brake is too weak, add more braking.
When the natural brake falls short, TLR7 and TLR8 fire against your own RNA, inflammation becomes chronic and tissue is damaged. In cutaneous lupus erythematosus (CLE), a form of lupus affecting the skin, that damage shows up as lesions and persistent inflammation.
Supporting evidence comes from genetics. Gain-of-function mutations in TLR7, meaning changes that make the sensor more active, are linked to lupus, and even modest increases in TLR7 signalling can drive lupus-like disease.
Noxopharm’s approach is to design oligonucleotides that mimic or amplify the body’s own braking fragments. Its first candidate, SOF-SKN, is a topical treatment being developed for CLE, with stated potential in psoriasis and dermatomyositis.
The logic is not unique to one company. A market research report dated 1 August 2026 describes selective inhibition of TLR7 and TLR8 as a recognised strategy against lupus.
You can see the same logic at work elsewhere on the ASX, where another autoimmune therapy has pursued immune restraint through a different target, showing that dialling down overactive immunity is a strategy several companies are testing.
Why topical delivery is part of the design
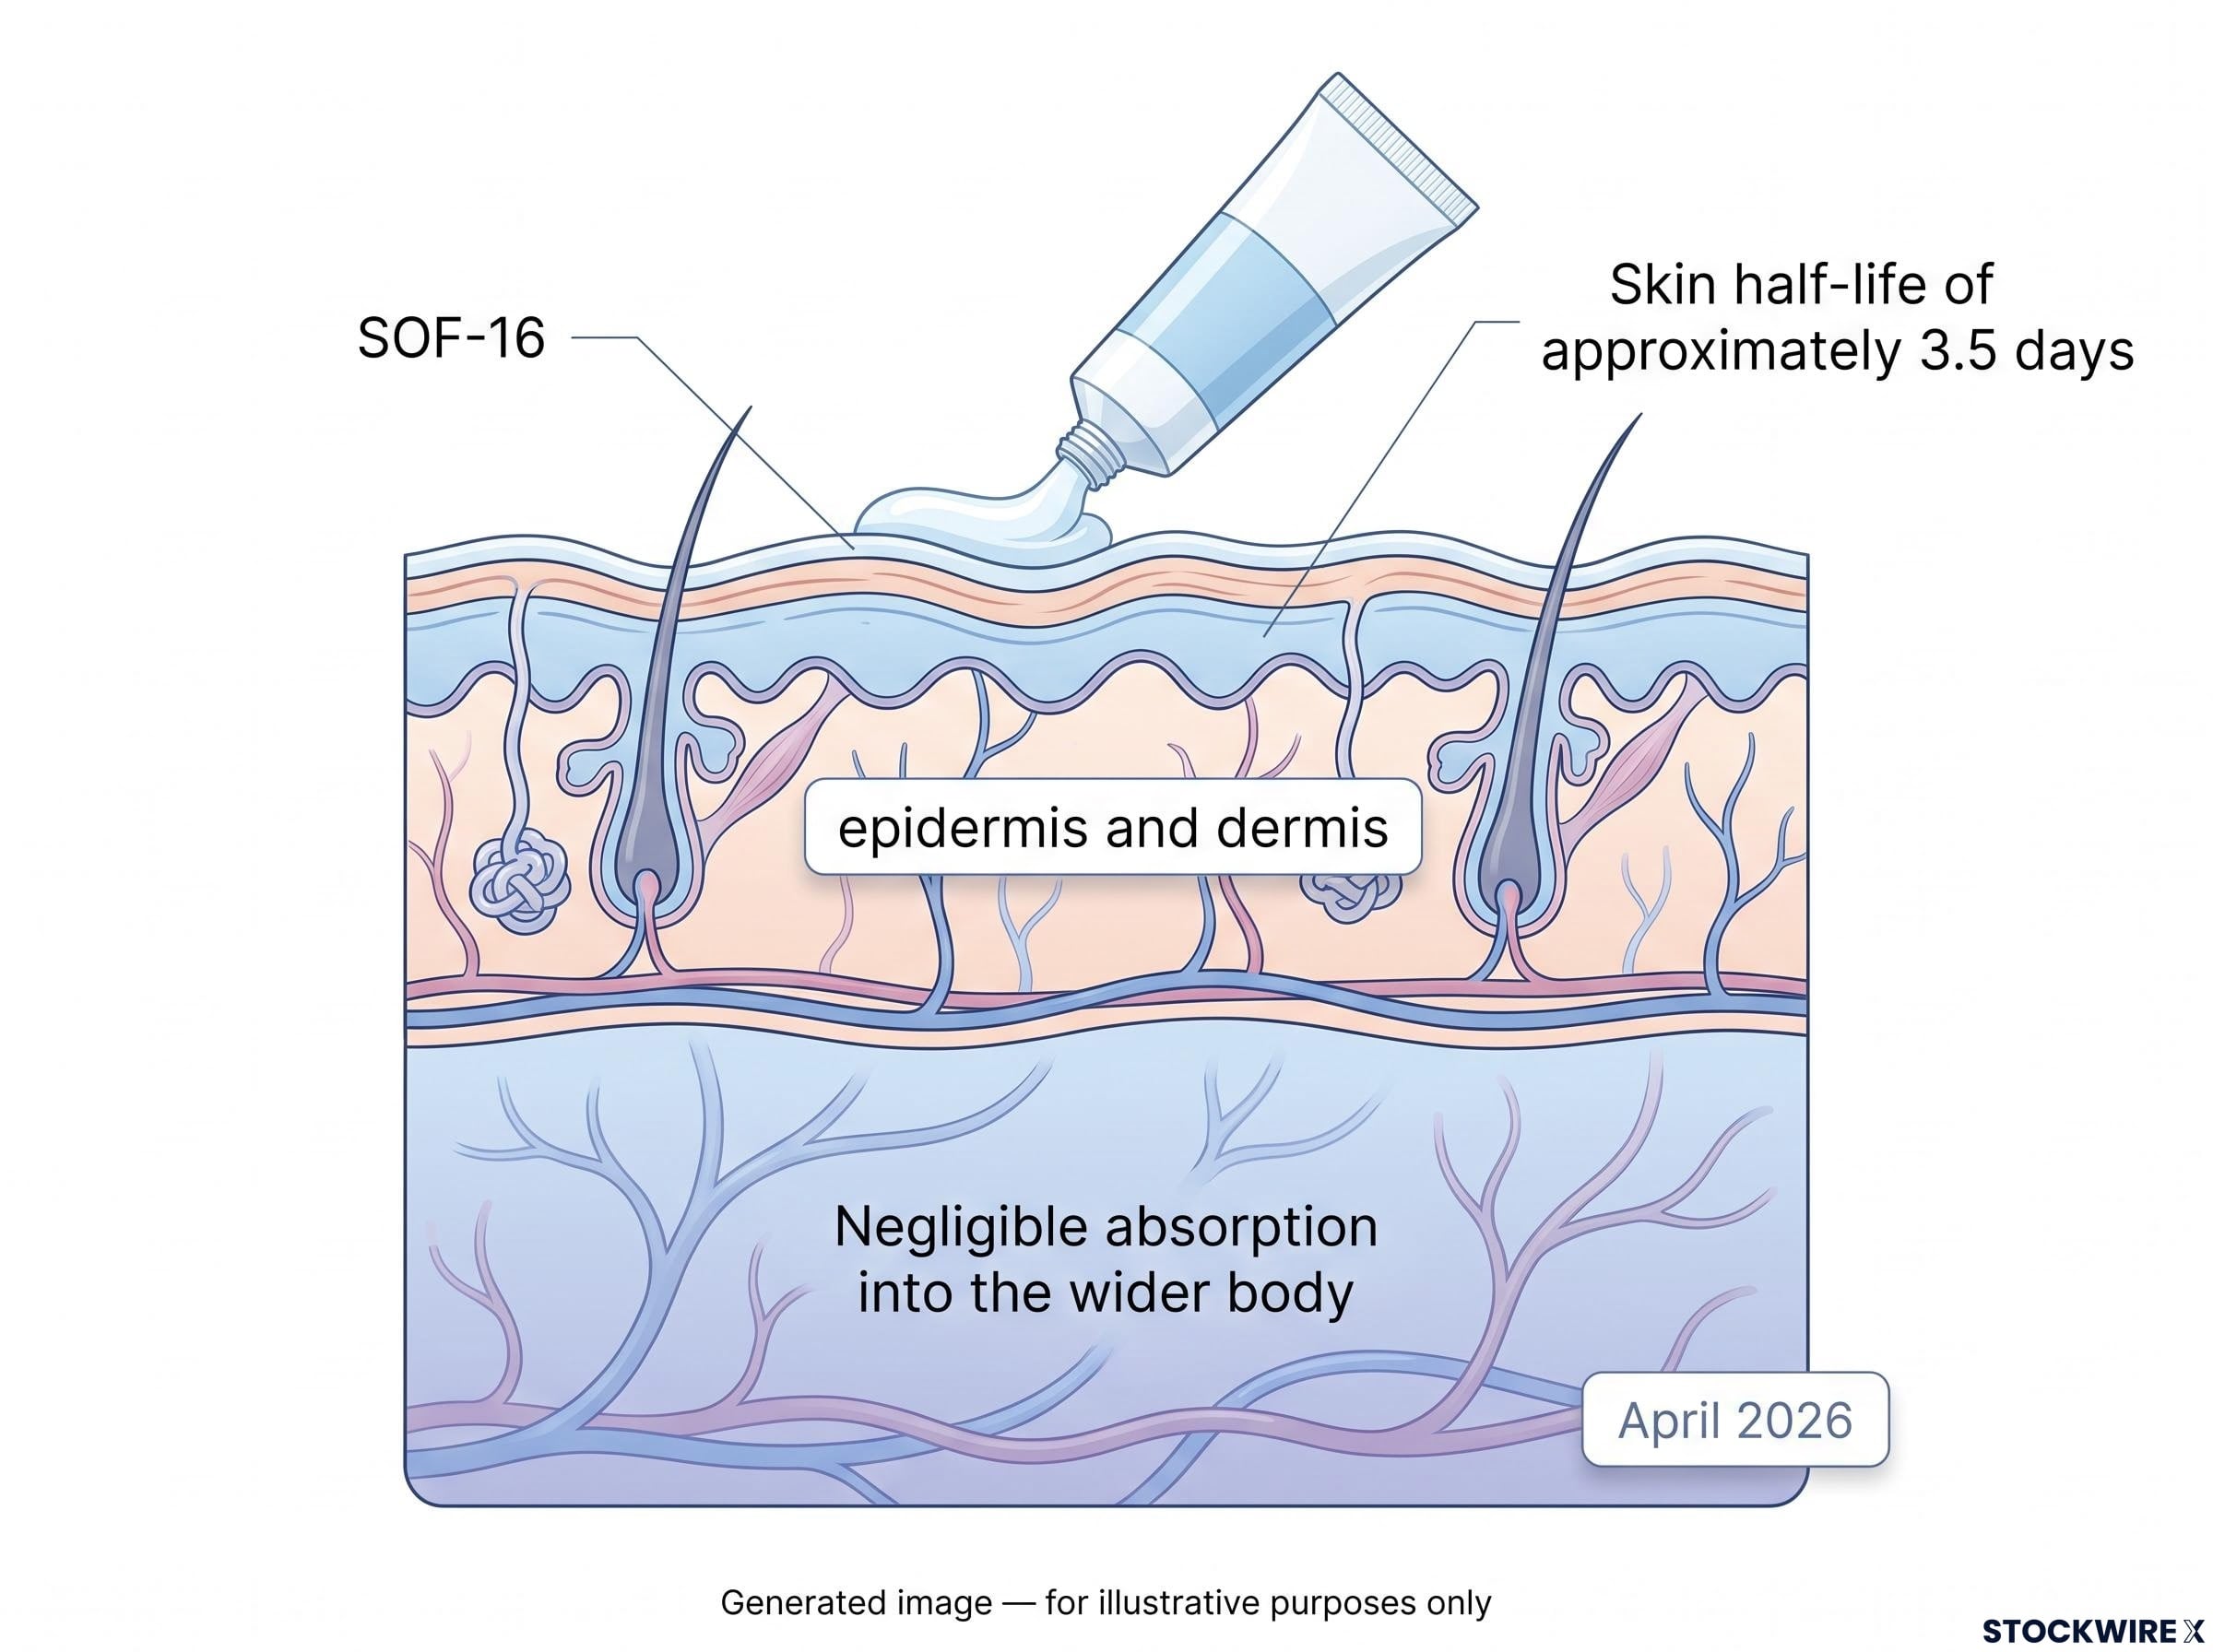
The intent is to quiet immune activation in the skin, not to suppress your immune system broadly. Preclinical data on the active ingredient, SOF-16, reported in April 2026 by the company, support that aim:
- Skin half-life of approximately 3.5 days in both normal and disease-like skin (preclinical)
- Largely confined to the epidermis and dermis, the outer and middle skin layers (preclinical)
- Negligible absorption into the wider body (preclinical)
There is a trade-off. Local delivery may limit benefit to lesions the cream can actually reach.
Most importantly, SOF-SKN has completed only a Phase 1 safety study, called HERACLES. Whether it works in patients has not been established. A targeted brake is a rational idea; rational is not the same as shown to work in people.
When the natural brake is too strong: a hidden tumour and the immune response
Now flip the picture. The same brake that protects you from lupus can help a tumour hide.
When cancer cells die, whether killed by your immune system or by treatment, they release RNA that could alert the immune system. That alarm is part of how your body learns to fight a tumour.
The problem is that this released RNA carries the same silencing signature. The sequence looks like this:
- A cancer cell dies.
- It releases its RNA.
- Tagged fragments in that RNA bind TLR7 and TLR8.
- The sensors stay inactive, and the tumour remains immune-silent.
- Boosting TLR8 activity can override the silencing.
That fifth step came from the researchers themselves, who found increasing TLR8 activity could overcome the effect. On 4 August 2026, Noxopharm and the Hudson Institute reported a laboratory result using TLR8-potentiating oligonucleotides from the company’s Sofra platform.
Preclinical, in vitro result In laboratory cell experiments, the immune response reached 437% of the level seen in untreated cells, according to Noxopharm. This is a dish measurement, not a patient outcome.
Gantier called the result a proof of principle: specific oligonucleotides, he said, can overcome the dampening effect that cellular RNA normally has on inflammation. The company says the data support combining this approach with chemotherapy and radiotherapy, since both kill cancer cells and release the RNA in question.
Read that 437% carefully. It shows the concept can work in a dish. It does not show it will work in you.
Why the same tool needs careful design
Releasing the brake is the mirror image of reinforcing it, and the line between the two is thin. A 2020 study found closely related 2′-O-methyl oligonucleotides could suppress TLR7 yet activate TLR8, depending on sequence.
Small design changes can turn a blocker into a stimulator. Existing medicine shows the stakes: topical TLR7/8 activators such as imiquimod are used in skin cancer, but the window between local benefit and inflammatory side effects is narrow.
One mechanism, one platform: where Sofra stands and what remains unproven
Put the two directions side by side and the central idea comes into focus.
| Aspect | Direction one: autoimmunity | Direction two: immune-silent cancer |
|---|---|---|
| State of the brake | Too weak | Too strong |
| Therapeutic goal | Reinforce it | Release it |
| Candidate or approach | SOF-SKN, topical, for CLE | TLR8-potentiating oligonucleotides |
| Evidence stage | Phase 1 safety completed | Preclinical, in vitro |
| Key caveat | Efficacy in patients not established | 437% is a laboratory figure only |
Same two sensors. Same type of tool. Opposite goals.
Why one mechanism makes a platform
Noxopharm describes Sofra as a platform with stated uses in inflammation, autoimmunity, oncology and mRNA drug enhancement. The mRNA logic follows the same path: inflammatory side effects of mRNA medicines involve these same sensors.
You should hold both halves of that idea. One validated body of science can yield several candidates, but every one of them depends on the same biology holding up in humans.
Where SOF-SKN currently stands
Noxopharm is a clinical-stage Australian biotech with two platforms, Sofra and Chroma, and the Hudson Institute as its strategic partner on Sofra. Dr Olivier Laczka became CEO on 15 April 2026, succeeding Dr Gisela Mautner, who resigned the day before; Fred Bart is Chairman.
After HERACLES, the company engaged clinical research organisation Novotech in May 2026, and flagged an extension study in CLE patients in September 2026. On 8 October 2026, it reported feedback from a pre-IND meeting with the US Food and Drug Administration (FDA).
A pre-IND meeting is a formal, early and non-binding discussion with the regulator about trial design, manufacturing and nonclinical requirements. The company says the FDA endorsed its proposed Phase II design and its CMC (chemistry, manufacturing and controls) approach. Independent searches found no public documents confirming the exact wording, and no Investigational New Drug (IND) application has been submitted.
A pre-IND meeting sits low on the milestone ladder, since regulator feedback at this stage shapes trial design but carries none of the weight of an approval or a designation, which is why such announcements need careful reading.
The company cites a CLE market worth more than US$3.3 billion, notes no therapies are specifically approved for CLE, and sees an Orphan Drug Designation opportunity. Those are company statements, and no designation has been granted.
What this does not tell you
- The paper validates a mechanism, not a drug.
- Oncology work is preclinical; the 437% figure is in vitro.
- SOF-SKN has passed Phase 1 safety only.
- Pre-IND feedback is not approval, permission to dose, or an FDA view on efficacy.
- Orphan Drug Designation has not been granted.
- A single-mechanism platform concentrates risk.
The wider field adds caution. TLR-targeting programmes have had mixed outcomes, and the step from mouse to human remains unproven here.
Immune regulation as a setting, not a switch
The bigger lesson is about how your immune system works. Regulation behaves less like an on-off switch and more like a dial. Turn it one way and you may treat autoimmune disease; turn it the other and you may make a tumour visible.
Autoimmunity and cancer immunology have historically been tackled by separate fields with separate tools. A single mechanism sitting behind both is unusual, which is why it deserves your attention.
Whether either direction becomes a medicine is a question only clinical trials can answer. Until then, keep the two kinds of evidence apart in your mind: expert scrutiny and publication in a leading journal is a different, more durable form of validation than a company announcement.
No commercial relationship exists with Noxopharm Limited. This content is general information only and does not constitute medical advice. This article is for informational purposes only and should not be considered financial advice. Investors should conduct their own research and consult with financial professionals before making investment decisions.
—